



Combining anavar and alcohol is not recommended while you are taking the medication. Both substances increase liver enzyme levels through overlapping metabolic pathways, and the risk does not disappear with a single drink. Oxandrolone is a prescription compound with documented clinical use in short-term supervised injury and recovery protocols, typically no longer than 8 weeks, and that clinical context requires the same caution around alcohol as any hepatically active medication. This article explains the specific mechanism behind the liver load, how long that risk persists after your last dose, and what warning signs mean it is time to contact your provider.
Why Anavar carries a specific liver risk
Oxandrolone is a 17α-alkylated oral androgen. That structural modification is what allows the compound to survive first-pass liver metabolism and remain active after oral administration. The tradeoff is direct: the alkylated molecule forces hepatic cytochrome P450 enzymes to process it, generating oxidative stress as a byproduct. A 2026 report in Case Reports in Hepatology documents this class effect of 17α-alkylated androgens, including cholestatic liver injury (PubMed).
The result is a documented rise in AST and ALT even at therapeutic doses used in short-course clinical protocols. That enzyme elevation is the core reason alcohol and Anavar should not be used together.
What 17α-alkylation means for your liver:
- Impaired bile flow as hepatocyte processing demands increase with the alkylated compound
- Elevated transaminases (AST and ALT) reflecting hepatocyte stress during metabolism
- CYP enzyme competition, reducing the liver's available capacity for other substrates
- Increased hepatocyte oxidative load from byproducts of the 17α-alkylation pathway
- Shorter protocol duration reduces cumulative exposure, which is why provider-defined endpoints matter
Does alcohol increase Anavar's liver toxicity?
Yes. Alcohol is metabolized by alcohol dehydrogenase and CYP2E1, both of which generate acetaldehyde and reactive oxygen species in the same organ already managing the 17α-alkylated compound. A 2023 review in the Journal of Translational Medicine details how CYP2E1-driven alcohol metabolism generates these hepatotoxic intermediates (PubMed). This is the "double hit" concept: two independent hepatotoxic loads competing for the same detoxification capacity, producing a combined effect greater than either alone.
The liver has a finite processing window at any given time. Layering alcohol onto an active oxandrolone protocol narrows that window for both substances. This is why the question of whether you can drink alcohol while taking Anavar consistently gets the same clinical answer across medical sources.

One drink vs. regular drinking: is there a safe amount?
No amount of alcohol is risk-free during an active short-course oxandrolone protocol. The mechanism-based distinction between occasional light drinking and regular or heavy consumption still matters for understanding how the risk scales.
A single standard drink creates a shorter, lower-intensity burden on hepatic processing. Regular or heavy drinking creates sustained CYP2E1 activation and chronic acetaldehyde production, which compounds the oxidative load from the alkylated compound in a more damaging pattern. Neither is safe during a protocol. They represent different categories of risk, not a safe zone and an unsafe zone.
What the anavar and alcohol risk means for protocol planning
The practical framing: this is a conversation to have with your provider before the protocol begins, not a personal risk calculation made during one. Any use of alcohol and Anavar in proximity should be disclosed upfront.
Factors that increase the risk of alcohol-Anavar liver stress:
- Baseline liver function that is already compromised before the protocol starts
- Protocol duration extending beyond the recommended short-course window (no more than eight weeks)
- Concurrent medications that also compete for CYP enzyme pathways
- Pre-existing conditions affecting hepatic processing capacity
- Frequency and volume of alcohol consumption during or adjacent to the protocol
A provider can review your baseline before a protocol starts. Get Started
Warning signs your liver is under stress
No major clinical resource on anavar and alcohol includes a symptom checklist tailored to the supervised-use setting. This gap matters for anyone on a supervised protocol.
The following symptoms are not a self-diagnosis tool. Each one is a reason to stop the protocol and contact your provider immediately. Do not wait for multiple symptoms to appear before acting.
Symptoms that require immediate provider contact:
- Nausea or vomiting not explained by other causes
- Dull or sharp pain in the upper right abdomen, where the liver sits
- Unusual fatigue that is disproportionate to your activity level
- Dark (cola-colored) urine, which can indicate elevated bilirubin excretion
- Yellowing of the skin or whites of the eyes (jaundice)
- Unexplained itching of the skin, a less recognized sign of bile duct stress
If any of these appear during or after a short-course protocol, stop and contact your provider. The combination of alcohol and Anavar raises the probability that any one of these signs reflects genuine hepatic stress rather than an unrelated issue.
For a broader look at which markers to track and why they matter, the guide on essential lab testing for hormone and peptide protocols covers the full monitoring picture.
The lab values that matter during a short protocol
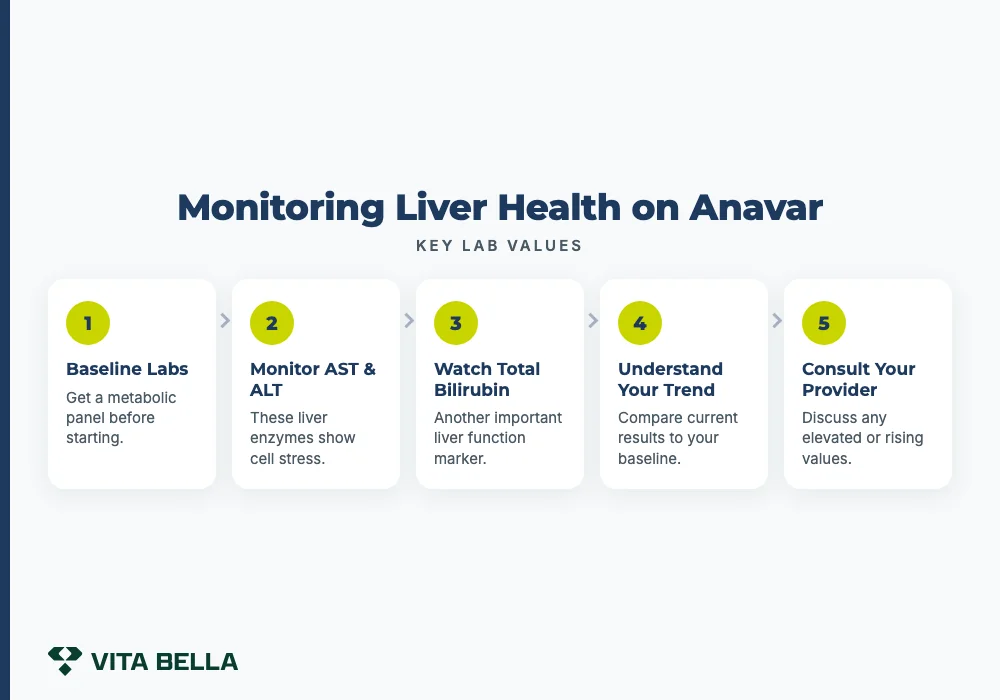
No clinical resource on this topic names the specific markers to monitor or explains what elevated results mean in practice. AST and ALT are the primary hepatic markers used during a short-course oral compound protocol.
Both are enzymes present inside liver cells. When hepatocyte stress causes those cells to release their contents into the bloodstream, AST and ALT levels rise. A provider-ordered metabolic panel before, during, and after a protocol catches this pattern early.
| Marker | Normal range | Mildly elevated | Contact your provider |
|---|---|---|---|
| AST | Under 40 U/L | 40–80 U/L | Above 80 U/L or rising trend |
| ALT | Under 56 U/L | 56–100 U/L | Above 100 U/L or rising trend |
| Total bilirubin | Under 1.2 mg/dL | 1.2–2.0 mg/dL | Above 2.0 mg/dL |
Reference ranges are general guidelines. A licensed provider determines clinical thresholds based on your individual baseline and trend, not any single value in isolation.
These numbers are context-dependent. A mildly elevated result in someone whose baseline was already at the high end of normal has different clinical significance than the same result in someone who started well below it. Baseline labs before a protocol are not optional for this reason.
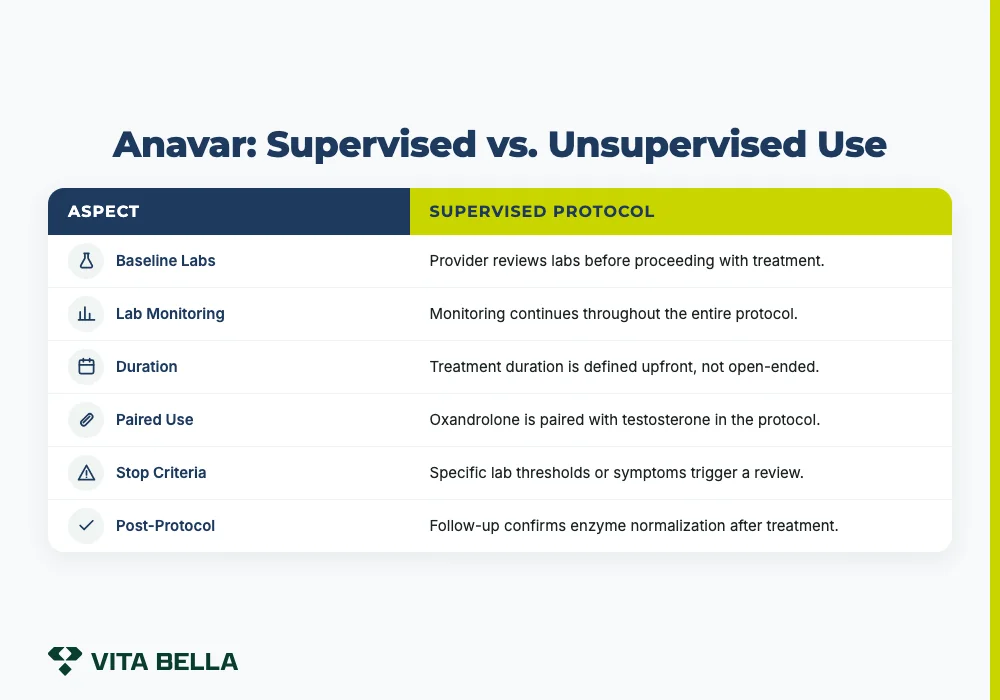
A provider-reviewed short-course oxandrolone program includes baseline and follow-up labs ordered and reviewed at each stage, with the provider determining whether any values are clinically significant. Labs are ordered and reviewed by the provider and billed separately.
Questions to ask your provider about labs before starting a short-course protocol:
- What is my current AST and ALT baseline, and is it safe to proceed?
- How often will labs be rechecked during the protocol?
- At what threshold will the protocol be paused or stopped?
- How long after the final dose should I recheck my liver panel?
- Are there concurrent medications I take that share CYP enzyme pathways?
- What is the plan if one hepatic marker rises while others remain normal?
What a standard hepatic monitoring panel includes:
- AST (aspartate aminotransferase)
- ALT (alanine aminotransferase)
- Total bilirubin
- Alkaline phosphatase (ALP)
- Gamma-glutamyl transferase (GGT)
Start with a provider evaluation before any protocol
If you are considering a short-course protocol for injury and recovery, a provider evaluation is the right starting point. You pick your provider, and they design a program around your labs.
A licensed provider reviews your baseline, determines whether the protocol is appropriate for your health history, monitors enzyme levels throughout, and adjusts or stops based on real data. Labs are ordered and reviewed by the provider and billed separately. Provider-supported programs include 1:1 provider care every quarter.
What a provider evaluation includes before a short-course protocol:
- Lab order: a full metabolic panel including hepatic markers before any protocol begins
- Provider review of lab results and health history to confirm whether proceeding is appropriate
- Protocol design based on your individual baseline and recovery goals
- Monitoring schedule with defined recheck points during the protocol
- Stop criteria: specific thresholds that trigger a pause or end to the protocol
Frequently asked questions
No. Both Anavar and alcohol stress liver detoxification pathways, and combining them elevates AST and ALT beyond what either causes alone. Any alcohol use should be disclosed to your provider before a protocol begins.
Most providers recommend waiting at least two to four weeks after the final dose, with timing based on post-protocol liver enzyme labs rather than drug half-life alone. Your provider will advise based on your specific results.
Key warning signs include nausea, right upper quadrant pain, unusual fatigue, dark-colored urine, and jaundice. Contact your provider immediately if any of these develop during or after a short-course protocol.
Alcohol does not directly block the compound's mechanism, but it competes for the same hepatic detox capacity and may worsen side effects. The added liver load undermines the conditions that make a supervised protocol safe to complete.
No. In a supervised short-course protocol, provider-ordered labs detect enzyme elevations before they become clinically significant. That detection layer is absent in unsupervised use, which is why the combination carries higher risk outside a clinical setting.
At minimum, a baseline metabolic panel that includes AST, ALT, and total bilirubin. Your provider orders and reviews the labs and determines the full panel based on your health history.
Sources
- Lou J et al. (2025). Oxandrolone for burn patients: a systematic review and updated meta-analysis of randomized controlled trials from 2005 to 2025. World Journal of Emergency Surgery. PubMed
- Ring J et al. (2020). Oxandrolone in the Treatment of Burn Injuries: A Systematic Review and Meta-analysis. Journal of Burn Care & Research. PubMed
- Case Reports in Hepatology (2026). Oxymetholone-associated cholestatic drug-induced liver injury. PubMed
- Journal of Translational Medicine (2023). Pathogenic mechanisms and regulatory factors involved in alcoholic liver disease. PubMed















